
Hyperthermia: A Treatment Possibility for Prostate Cancer
by Friedreich R. Douwes, MD
Introduction
Early detection of prostate cancer (PC), as, in all malignancies, is very important, so that with appropriate therapy the chances of a cure increase. The prostate cancer screening guidelines suggest, besides surgical removal of the prostate (prostatectomy) and the various forms of radiation, monitoring the patient through “active surveillance.” This controlled and regularly executed observation is especially used in patients with a slow-growing tumor (so-called insignificant prostate cancer). This type of prostate cancer is characterized by minor tumor volume and less aggressive growth. The latest studies show that the results of the active surveillance are as good as after invasive procedures, such as surgical removal of the prostate or radiation.
Many men diagnosed with prostate cancer have a rather good chance of never requiring active treatment. The slow-growing tumors in these patients usually do not compromise their life expectancy. However, since many men psychologically cannot tolerate a “wait-and-watch” approach after they have been diagnosed with cancer, there is considerable interest in finding an alternative with relatively few side effects. For decades now at St. George Hospital, we have had excellent clinical results using urethral thermotherapy (also known as transurethral hyperthermia with radiofrequency waves). We combine this with temporary hormone therapy.
What Is Transurethral Hyperthermia and Why Is It Combined with a Temporary Hormone Therapy?
Hormone therapy alone does not confer a survival advantage.
An important study published in JAMA by Grace L. Lu-Yao et al. of the Robert Wood Johnson Medical School (New Brunswick, NJ) has questioned the efficacy of this widely used form of treatment.1 In this study were a total of 19,271 mostly elderly men (with a median age of 77) with cancer limited to the prostate (known as T1 and T2 tumors). Men who received primary hormone treatment were compared with an equal number of men without treatment, so-called active surveillance. One surprising result was that hormonally treated patients survived no longer than those who received no active treatment. The 10-year overall survival rates were 30.2% in the treated and 30.3% in the untreated groups; that is, virtually identical in both groups. More surprising, the prostate-cancer specific survival was actually lower in the hormone-treated group than in the no-treatment controls (80.1% vs. 82.6%).
Because the patients treated were mostly elderly with cancer limited to the prostate, the authors recommended restraint with long-term hormone therapy, as it is associated with enormous health risks such as increased bone fragility, diabetes, heart disease, and impotence. The authors also mentioned: “Maybe the survival time is not the sole goal, quality of life is also of importance.”1 In this therapy are also economic aspects. In 2008 alone, the US spent $1.3 billion for hormone treatments. The German and European numbers are similarly high.
Prostate cancer, together with bronchial cancer, is one of the most common forms of this disease in men. The average age at diagnosis is over 70 years. Given the absence of early symptoms of cancer, it was usually only discovered in the early stages by chance, but this has favorably changed in the PSA era (i.e., since 1990).
In a subset of patients with poorly differentiated PC, there was a slight improvement in PC-specific survival, but this did not carry over into overall survival.
The recommended therapy for prostate cancer depends on the stage of the disease and the general condition of the patient. With localized, nonmetastasized prostate cancer, in most cases active surveillance is the best approach. The survival rate, especially in elderly patients with a limited life expectancy, would not improve with a radical prostatectomy, even with possible resection. However, such a procedure would reduce quality of life, with incontinence and impotence.
Little Difference in Survival Times
A large survey of urologists and radiation oncologists in the US has shown that over 90% of urologists recommended radical surgery and the vast majority of the radiation oncologists recommend radiation therapy.2 This disparity suggests that there is no “best therapy” and that it may be difficult for the patient to make a rational therapy decision. However, since prostate cancer, due to its slow growth, does not make an immediate treatment decision necessary, the patient should choose the therapy that, after extensive research, promises the best conditions for a good quality of life and few side effects.
In the largest such study since the introduction of routine PSA testing , Lu-Yao has shown that the results of watchful waiting with prostate cancer are so good that it is questionable whether invasive measures can still make an improvement.
80% of Patients Are Impotent After Radical Surgery
The potential impact should also be considered with surgery. For instance, the urinary sphincter may be damaged and the patient will thereby suffer from incontinence. Another serious consequence is impotence, which occurs in approximately 80%. Pursuing a watchful-waiting approach leads to only about half of the patients’ experiencing impotence. After a radical prostatectomy, every second patient experiences urinary incontinence (49%), but with “wait and see” management, this occurs onl nly his only 5 men (21%).4
Impotence (defined as an erection weakness) is an essential quality-of-life factor that should be considered in treatment choice, even if there is a significant survival advantage after radical therapeutic measures. However, even with expectant management, we can anticipate problems. A bladder-emptying disorder may develop during the course of a slow-growing prostate cancer, because the expanding tumor presses on the urethra, decreasing its size. This urination problem occurs in 44% of the patients, but can be somewhat remedied
.
Prostatectomy with Radiation Therapy Combined?
If you look at recent studies, it is clear that because of diligent PSA testing, more early-stage tumors are found as compared with older examinations. Only in advanced stages (T3 prostate cancer) does surgery in combination with radiation therapy offer a better survival time, as shown in the Ulmer Multicenter Study.5 Also, other studies (Figure 1) attest to the fact that only patients in advanced stages wherein positive margins during operation were found benefit from additional radiation therapy.6
Figure
1
Alternative: Transurethral Thermotherapy with a Time-Limited Complete Androgen Blockade
Despite the slow growth and long, sometimes inconspicuous clinical characteristics of prostate cancer, in a few cases can spontaneous proliferation and metastasis arise, and subsequently the window of opportunity for a curative treatment is missed. Many patients know this and are understandably afraid of the consequences. So, they justifiably look for alternatives.
Transurethral hyperthermia (i.e., heat therapy guided through the urethra) can be an additional alternative in such cases, especially when it is combined with temporary hormone therapy. Prostate cancer proves to be extremely sensitive to heat. Two treatments of three hours and an average temperature between 48 and 52 ºC (118.4–125.6 ºF) in the prostate kill most of the localized prostate cancer.
To keep the local area tumor free and to prevent remaining tumor cells from growing, at St. George Hospital we combine this method with hormone therapy given for 6 to 9 months.
Thanks to Transurethral Thermotherapy, No Permanent Side Effects
Transurethral hyperthermia leads to massive tumor cell destruction due to the high temperatures that we achieve in the prostate with a computer-controlled radio frequency device (OncoTherm EHY 1020
)
. The technology of this device is based on the generation of short waves and an electromagnetic field, where the tumor cell destruction results from both the heat and the electric field (Figures 2– 4).
Figure
3

Figure 2
Figure
4

The former, microwave devices often used in urology, are unsuitable for tumor treatment because they are not capable of heating the prostate evenly because of their low penetration and some other unresolved technical problems.
Furthermore, these devices produce too many complications. Radio frequency hyperthermia, also known as oncotherapy, allows specifically for the heating of the cancer tissues, which has different impedance than healthy tissue. Thus, the radio waves are absorbed more by the cancer tissue which becomes very hot and dies off, the so-called apoptosis (programmed cell death). This process also causes increased “heat shock proteins” in the cancer cells. These are special proteins that occur whenever cells come under stress or age. Especially the immune system recognizes, destroys and discards these charged cells. By heat treatment, we generate these heat shock proteins, particularly in the cancer cells. These cells not only die as a result of overheating, but are also increasingly recognized by the body’s own immune system which in turn attacks and destroys them. This form of heat treatment not only destroys the prostate tumor, but also induces a specific immune response.
Of course, this also shows the fundamental difference from conventional therapies.
First, during an operation is the tumor removed from the body and thus also important information for the immune system. Second, this is a major trauma that provokes inflammation and the release of growth hormones that encourages still present cancer cells to grow. With the, through the urethra guided, heat treatment dies the tumor within the organ and the surrounding healthy tissue is not damaged and remains fully functional. The body’s own immune system is stimulated to recognize and battle the tumor. The usual side effects of surgery and radiation do not occur in hyperthermia. Even for these reasons alone, hyperthermia is a real alternative to watchful waiting. In other words, for the qualified patient, it is still better to conduct an effective method with few side effects than to wait and see if the tumor is growing, even when for this approach studies with larger numbers are still pending. The patient’s quality of life is improved by it, especially while potency problems and urinary incontinence do not occur with hyperthermia.
Given the fact that so far none of the conventional therapies offer significant survival advantage for prostate cancer patients, it may be difficult to impose a specific invasive procedure with irreversible damage on a patient. Rather, the patient should have a say in what he wants, especially when you take into consideration the possibility of a dramatic impairment life quality.
We combine the already very effective transurethral heat therapy with a temporary hormone therapy. Why? Because it has been shown that in most patients already had a transrectal multibiopsy during which not only were the malignant cells washed into the system, where they lodged in the lymph nodes or bone marrow, but the biopsy insult also induced local prostate inflammation followed by a healing process during which many mediators are
released such as growth hormones (e.g., EGF, VEGF, COX-2).
The biopsy injury to the prostate must heal and for this are inflammatory mediators and growth hormones needed. But precisely these mediators produce in a less vicious tumor a faster and aggressive growth of the tumor and thus feed a general activation. Therefore, we offer our patients an injury-free diagnosis of prostate cancer; that is to say, we replace when needed the biopsy with molecular genetic testing and appropriate imaging techniques. One can also abstain from the traumatizing biopsy because even for a positive diagnosis usually only watchful waiting is recommended. So why should a man risk a carryover of tumor cells, or tumor activation, or even a local infection, if they have no therapeutic consequences?
We start the hormone therapy shortly before and continue up to 6 months after the heat therapy with it. What is their function? Hormone therapy prevents the in the body remaining cancer cells from growing. Also, there remains sufficient time for the hyperthermia induced immunological effects to become active.
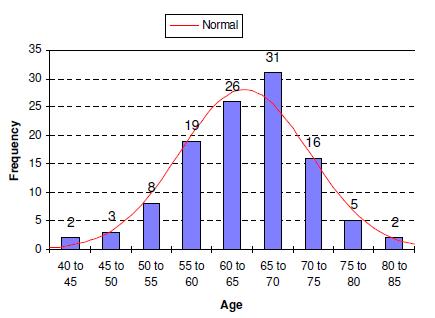
To be precise, with this method we not only destroy the malignant tumor cells in the prostate, but we also trigger an active specific immune response. Due to the temporary hormone therapy, we achieve a growth hormone inhibition of cancer cells outside of the prostate. The treatment itself is well tolerated, without complications and pain free. It takes place on outpatient basis and does not require hospitalization. In 1998, we have treated 123 patients (Table 1) according to this protocol (2- to 3-hour-long hyperthermia treatments through the urethra with 6 months of hormone therapy) and followed them for 10 years. Patients entered the study with a mean age of 71. Prostate cancer was confirmed in all patients by biopsy, and metastases were excluded by environmental studies. All patients were in full remission 6 months after initiation of the therapy and had normal PSA values, after which the hormone therapy was discontinued. In 85% of the patients, this good treatment outcome remained over the entire observation period of 10 years. The therapy was repeated in 15% of the patients because at one time or another they showed PSA recurrence. During the 10-year observation period, 16 patients out of this group died from other diseases, but not from prostate cancer. Two patients were treated with TURP (transurethral resection of the prostate) surgery for urination problems. There were no tumor cells in the prostate tissue that was removed, although more than 5 or 7 years before prostate cancer was confirmed by biopsy.
Table 1:
Treatment protocol for prostate cancer limited to the prostate (T1/T2).
No hospitalization necessary; outpatient procedure.
Days |
||||||
Transurethral hyperthermia3 hours at 48–52º C |
1 P-Hy |
2 |
3 P-Hy |
4 | 5 | |
Triple therapy with hormones* |
For 6 months | |||||
Hormone Balancing After Care |
Months after treatment |
|||||
| 1½ | 3 | 6 | 12 | 18 | 24 | |
Checkups PSAControl |
× | × | × | × | × | × |
PCA3 test |
× | × | × | |||
*
GMRH-beock antiandrogen 5-α – reductase inhibition
Comparative Study Planned by the Usual Methods
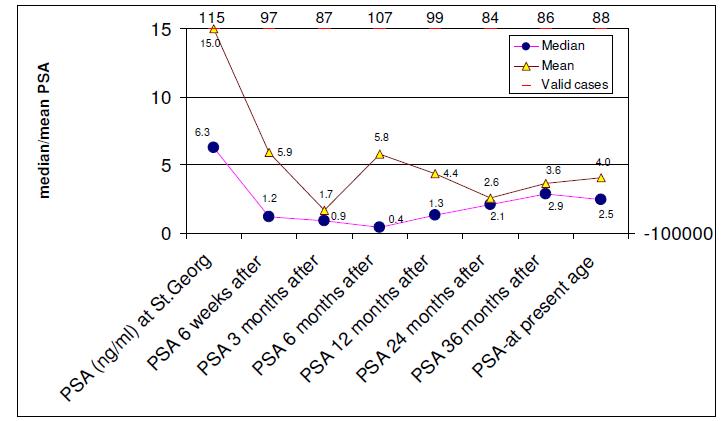
In summary, it can be said that even if the guidelines suggest something else, currently there is no best therapy for localized prostate cancer. For that reason, physicians refrain from immediately operating or irradiating each prostate carcinoma, because these invasive therapeutic measures are associated with significant side effects and marked reduction in quality of life. Alternatively, it is proposed to use the active surveillance method, since prostate cancer usually has a long clinical course. However, there are a few cases wherein it spontaneously proliferates and metastasizes, and then an appropriate therapy can be missed. Many patients are aware of this problem and are therefore searching for other treatment options. A side-effect-free alternative could be hyperthermia in combination with temporary hormone therapy. We achieved good results with this therapeutic approach as exhibited in our 10-year study during which 85% of the patients showed complete remission and only 15% had a PSA recurrence.
Figure
5
Figure
6
It is intended, in another controlled, prospective study, to compare hyperthermia in conjunction with temporary hormone therapy with other common forms of treatment in order to finally shed some light on comprehensive long-term results. If active surveillance with its known risks is permitted, then hyperthermia with temporary hormone treatment should also find its place among the standard therapies, because no substantial, lasting adverse effects are incurred. To the contrary, it increases quality of life and life expectancy.
Notes
-
Lu-Yao G et al. Survival following primary Androgen Deprivation Therapy among men with localized prostate cancer. JAMA. 2008;300:173–181.
-
Fowler F et al. Comparison of recommendations by urologists and radiation oncologists for treatment of clinically localized prostate cancer. JAMA. 2000;283:3217–3222.
-
Lu-Yao G et al. Outcomes of localized prostate cancer following conservative management. JAMA. 2009;302:1202–1209.
-
Steineck G et al. Quality of life after radical prostatectomy or watchful waiting. N Eng J Med. 2002;347:790–796.
-
Wiegel T et al. Phase III postoperative adjuvant radiotherapy after radical prostatectomy compared with radical prostatectomy alone in pT3 prostate cancer with postoperative undetectable prostate-specific antigen: ARO 96-02/AUO AP 09/95. J Clin Oncol. 2009;27:18:2924–2930).
-
Van der Kwast Th et al. Identification of patients with prostate cancer who benefit from immediate postoperative radiotherapy: EORTC 22911. J Clin Oncol. 2007;25:27:4178–4186.
LEGEND
Figure 1. Survival curve of patients in advanced stages with negative and positive section margin (SM).
SM negative surgery only and then “wait and see.” SM negative plus radiation shows no advantages over wait and see. Patients with positive resection margins profit from an additional radiotherapy and achieve similar results as patients with negative resection margins (SM).
Figure 2 The EHY 1020 from OncoTherm, a radiofrequency machine for transurethral hypothermia of the prostate, is in use now at St. George Hospital.
Figure 3 Shows the treatment catheter in the right position in the center of the prostate. The electrode emits radio waves, which penetrate the normal and healthy prostate tissue easily, but is absorbed to a normal and higher extend from cancerous tissue, which then gets selectively heated up to 52 ºC (125.6 ºF). Important is the counter electrode around the hips to establish an electromagnetic field.
Figure 4 Demonstrates the difference between microwaves, respectively radio waves (shock waves) for prostate-hyperthermia and radiofrequency. In microwave hyperthermia, the waves radiate with high energy directly into the tissue, but have only a penetration depth of 1–2 cm. Inside the urethra and at the rectal mucosa, a sophisticated cooling is used. Radio waves, as used in the OncoTherm system, go easily through healthy tissue, but caught in the dense cancer tissue they are converted into heat. It is a self-processing system. Only, the electrodes get warm and no cooling is used. So injuries to the urethra and sphincters are not possible.
Figure 5 The course of PSA after the transurethral hyperthermia.
Figure 6 Age distribution of our patients treated by transurethral radiofrequency hyperthermia (TURF).








0 Comments